
Set-back suture technique
How to place a set-back dermal suture, and when to use it.
Surgery · Operative techniques
Set-Back Suture Technique – Summary for Surgery Residents
Application
- Ideal for high-tension areas: back, shoulders, thighs.
- Can be used nearly anywhere, including central face, ears, cheeks, and forehead.
- Suitable for areas prone to wound inversion.
- Easier to place than buried vertical mattress; appropriate for students and residents as a primary deep tension-relieving technique.
Suture Material Choice
- Back: 2-0 absorbable (thicker suture tolerated; rare suture spitting).
- Extremities: 3-0 or 4-0 absorbable.
- Face/low tension areas: 5-0 absorbable.
- Thicker suture acceptable as it is buried deep in dermis.
Technique Steps
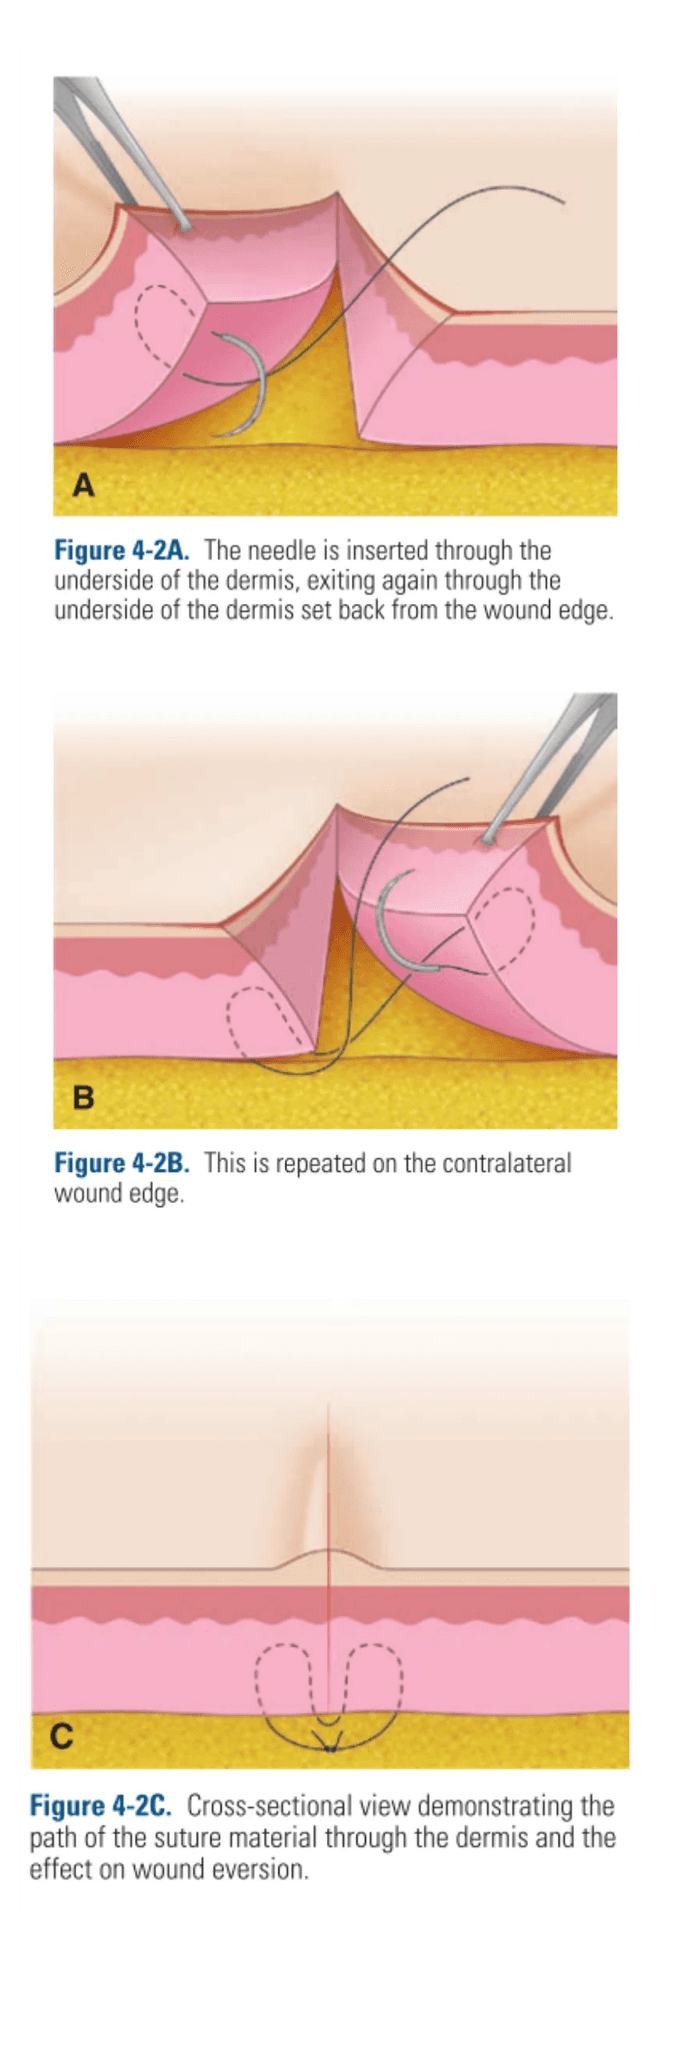
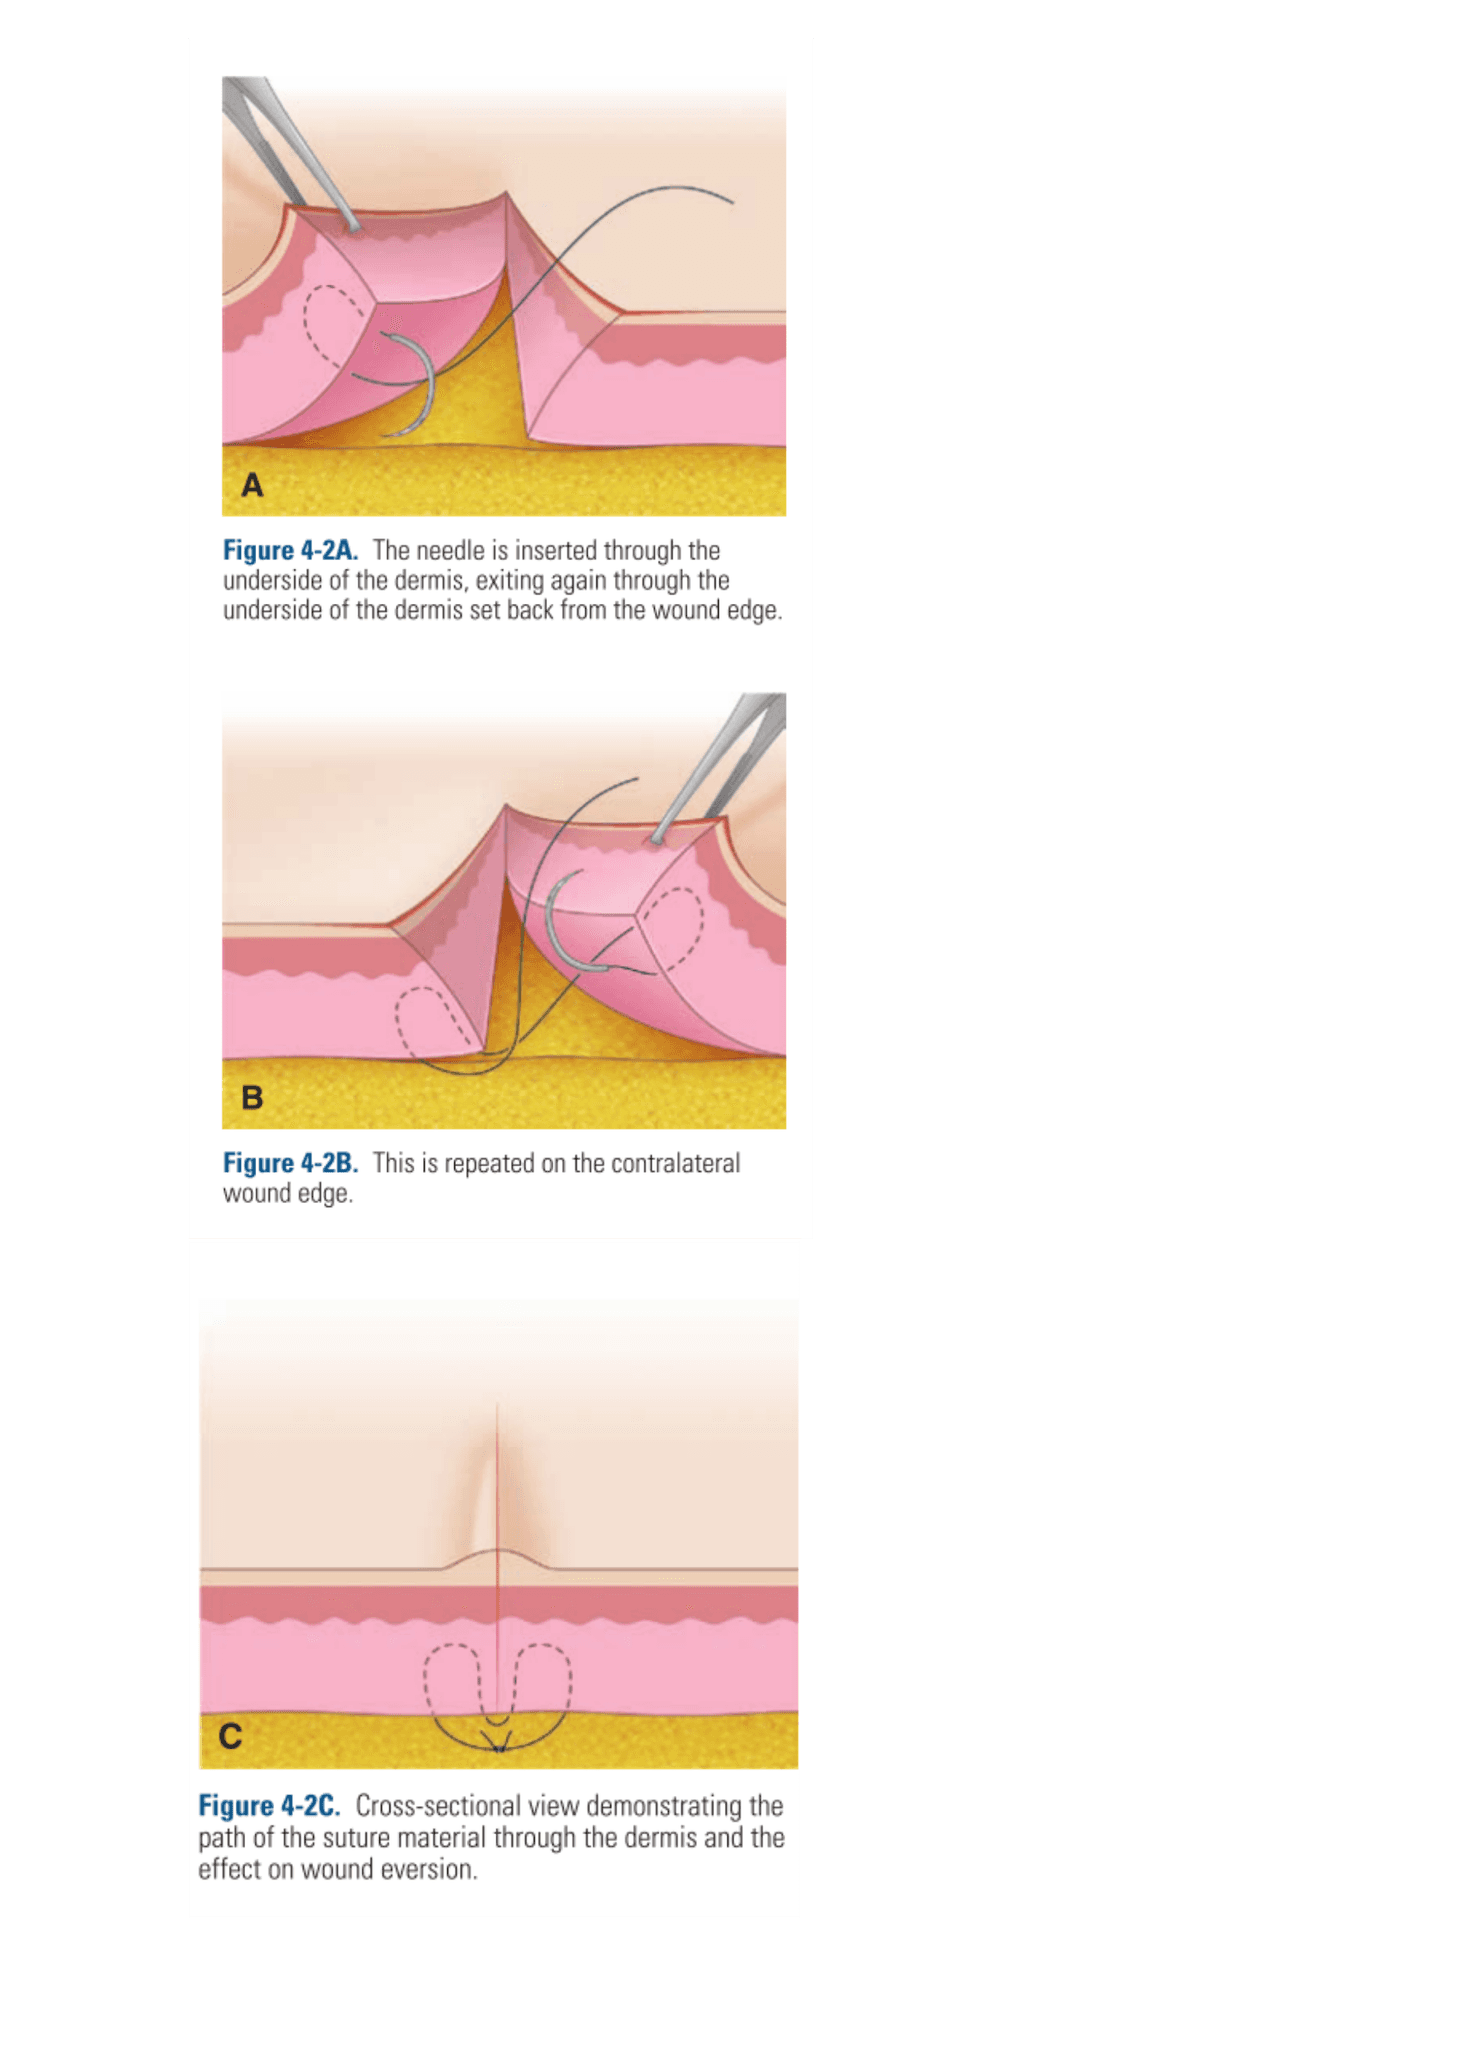
1. Reflect wound edge with forceps/hooks for dermal visualization.
2. Insert needle at 90° into dermis, 2–6 mm from wound edge.
3. First bite: follow needle curve through dermis, exiting 1–4 mm from wound edge.
- Avoid epidermis to prevent dimpling.
4. Release first side; reflect opposite edge to visualize dermis underside.
5. Second bite: mirror the first; insert 1–6 mm from wound edge, exit 2–6 mm distal.
- Avoid epidermis.
6. Tie suture using an instrument tie.
---
Images
Tips and Pearls
- Superior eversion and cosmesis compared to buried vertical mattress (based on randomized trial).
- Easier execution: follows needle arc; no need to change planes or perfect exit point.
- Requires broad undermining to allow full loop under dermis.
- Useful for dead space reduction (e.g., cyst/lipoma excision):
- Set first bite further back to reduce central laxity and increase wound ridge.
- Chest keloids: Combination with post-op electron beam irradiation achieved ~98% success.
- Effect attributed to tension reduction and deep suture placement away from wound edge.