62. Gastric volvulus, gastroptosis, bezoars and foreign bodies
High yield
Twisting, sagging and blockage of the stomach; volvulus is an emergency, most swallowed objects pass on their own.
Exam Prep · State examSurgery · Upper GISurgery · Emergency and trauma
1. Definition
- Gastric volvulus → rotation of the stomach of more than 180° around one of its axes, causing obstruction and risk of strangulation
- Gastroptosis → downward displacement of the stomach (visceroptosis), often with other organs
- Bezoar → mass of undigested material that collects in the stomach or bowel
- Foreign body → swallowed (ingested) object, by accident or on purpose
2. Epidemiology
- Gastric volvulus → rare; peak age over 50 (adults), 15–20% in children under 1 year (with diaphragmatic defects)
- Gastroptosis → thin, tall women; often with general visceroptosis
- Bezoars → rare; most after gastric surgery (vagotomy, gastrectomy) or with gastroparesis; trichobezoars in young women with psychiatric illness
- Foreign bodies:
- 80% in children (6 months–3 years): coins, button batteries, magnets, toys
- Adults → food bolus, dentures, fish and chicken bones; prisoners, psychiatric patients, drug packers
- 80–90% pass spontaneously; 10–20% need endoscopy; about 1% need surgery
3. Aetiology and risk factors
Gastric volvulus
- Primary (about 1/3) → lax or absent gastric ligaments (gastrosplenic, gastrohepatic, gastrocolic, gastrophrenic)
- Secondary (about 2/3) → anatomical defects:
- Paraoesophageal hiatus hernia (most common)
- Diaphragmatic eventration, traumatic rupture, CDH
- Asplenia, wandering spleen, adhesions
Gastroptosis
- Weak abdominal wall, rapid weight loss, multiple pregnancies, thin body build
Bezoars
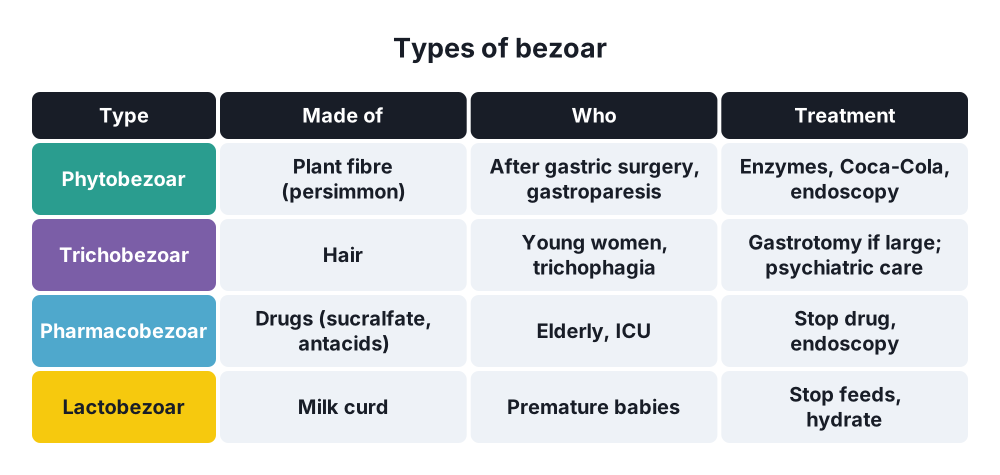
- Phytobezoar → plant fibre (persimmons, citrus, celery); after gastric surgery, diabetes
- Trichobezoar → hair; trichotillomania and trichophagia; young women
- Pharmacobezoar → drugs (sucralfate, antacids, extended-release tablets)
- Lactobezoar → milk curd; premature babies on concentrated feeds
- Others → shellac, plastics, tissue paper
- Risk → poor gastric emptying, low acid, poor chewing, no teeth
Foreign bodies
- Children → putting things in the mouth
- Adults → dentures, alcohol, mental illness, learning disability, prisoners, body packers (drug packets)
- Narrowing → oesophageal stricture, eosinophilic oesophagitis, ring
4. Pathogenesis
- Volvulus:
- Stomach twists over 180°
- Closed-loop obstruction at the cardia and pylorus
- Venous congestion, then arterial cut-off
- Ischaemia, necrosis, perforation (5–28%)
- Gastroptosis → stomach hangs low; slow emptying; dragging pain
- Bezoar → grows slowly; can obstruct the pylorus; trichobezoar may extend into the small bowel as a "tail" (Rapunzel syndrome); pressure ulcers and bleeding
- Foreign bodies → narrow points:
- Cricopharyngeus (most common hold-up point)
- Aortic arch and left main bronchus
- Lower oesophageal sphincter
- Pylorus, duodenal C-loop, ligament of Treitz, ileocaecal valve
- Button battery → electric current makes hydroxide at the mucosa → liquefactive necrosis within 2 hours; perforation, aortic or tracheal fistula
- Two or more magnets → attract across bowel walls → pressure necrosis, fistula
- Sharp objects → perforation (15–35% if not removed)
5. Classification
Gastric volvulus
- By axis:
- Organoaxial (about 2/3) → around the long axis (cardia to pylorus); greater curve flips up; adults, with hiatus hernia
- Mesenteroaxial (about 1/3) → around the short axis (lesser to greater curve); antrum rotates up; children, chronic
- Combined (rare)
- By onset → acute, chronic (intermittent)
- By cause → primary, secondary
Bezoars
- Phyto, tricho, pharmaco, lacto, others
Foreign bodies
- Blunt, sharp-pointed, long (over 6 cm), button batteries, magnets, food bolus, drug packets
6. Clinical picture
Symptoms
- Acute gastric volvulus → Borchardt's triad:
- Severe sudden epigastric pain and distension
- Retching with little or no vomiting
- Inability to pass an NG tube
- Chronic volvulus → intermittent epigastric fullness, early satiety, bloating, chest pain after meals
- Gastroptosis → dragging pain after meals, relieved by lying down; bloating, constipation
- Bezoar → early satiety, nausea, vomiting, epigastric pain, weight loss; may be silent; bleeding, obstruction
- Foreign body:
- Oesophagus → dysphagia, odynophagia, drooling, inability to swallow saliva, chest pain, retching
- Children → may be silent; refuse feeds, drool, stridor, cough
- Stomach and below → usually no symptoms; pain, fever, peritonitis if perforated
Signs
- Volvulus → epigastric distension; shock and peritonitis if strangulated
- Bezoar → movable epigastric mass (trichobezoar), patchy hair loss, foul breath
- Foreign body → neck tenderness, surgical emphysema (perforation), peritonism
7. Diagnosis
- Volvulus:
- Chest and abdominal X-ray → large gas-filled viscus in the upper abdomen or chest, double air-fluid level
- CT → transition point, position, ischaemia, hiatus hernia
- Contrast meal → type of volvulus (chronic)
- Endoscopy → may untwist; check mucosa
- Gastroptosis → barium meal standing: low J-shaped stomach (greater curve below the iliac crests)
- Bezoar → endoscopy (diagnostic and therapeutic); CT (mottled mass with gas); barium meal (filling defect)
- Foreign body:
- Plain X-ray neck, chest and abdomen (AP and lateral) → most metal objects
- Button battery → double ring (halo) on AP view, step-off on lateral (coin has none)
- CT → radiolucent objects (bones, plastic), perforation, drug packets
- No barium (makes endoscopy hard; aspiration risk)
- Metal detector in children (coins)
8. Differential diagnosis
- Volvulus → acute pancreatitis, perforated ulcer, myocardial infarction, oesophageal rupture, mesenteric ischaemia
- Gastroptosis → functional dyspepsia, gastroparesis
- Bezoar → gastric tumour, gastric outlet obstruction
- Foreign body → oesophageal spasm, globus, food impaction on a stricture or cancer
9. Treatment
Conservative
- Acute volvulus:
- Resuscitation, analgesia
- NG decompression (if it passes)
- Endoscopic reduction in selected patients without ischaemia; percutaneous endoscopic gastrostomy (PEG) to fix it (gastropexy) in unfit patients
- Gastroptosis → reassurance, small frequent meals, lie down after meals, abdominal support, physiotherapy of abdominal muscles; surgery almost never
- Bezoars:
- Phytobezoar → enzyme dissolution (cellulase, papain) or Coca-Cola lavage, prokinetics (metoclopramide)
- Endoscopic fragmentation and removal (snare, basket, lithotripsy)
- Treat the cause → gastroparesis, diet, psychiatric care (trichobezoar)
- Foreign bodies:
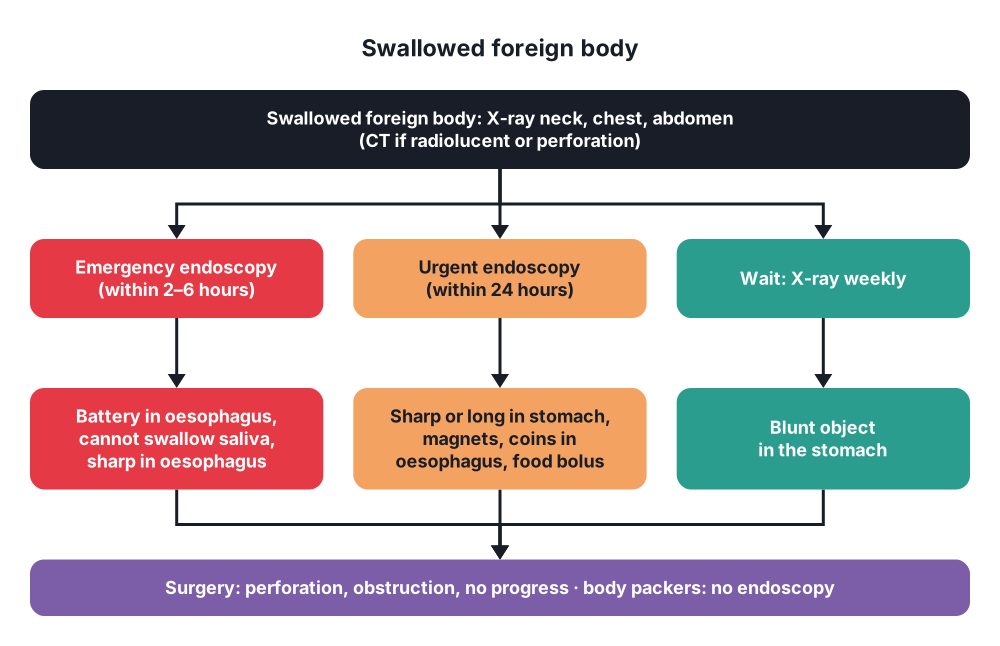
- Blunt object in the stomach → wait; X-ray weekly; most pass in 4–6 days
- Endoscopy timing:
- Emergency (within 2–6 hours) → button battery in the oesophagus, oesophageal obstruction (cannot swallow saliva), sharp object in the oesophagus
- Urgent (within 24 hours) → sharp or long objects in the stomach, magnets, oesophageal coins, food bolus
- Elective → blunt objects stuck in the stomach over 3–4 weeks
- Food bolus → glucagon or effervescent agents (weak evidence); endoscopy with push or retrieval; then biopsy for eosinophilic oesophagitis or stricture
- Endoscopy with an overtube for sharp objects
- Battery in the stomach in a child → remove if symptoms, large (20 mm or more) or under 6 years with magnet; otherwise X-ray in days
- Honey or sucralfate for a swallowed button battery in a child over 1 year, while waiting (within 12 hours)
- Body packers → conservative with laxatives and watchful care; no endoscopy (packet rupture → drug overdose)
Surgical
- Acute volvulus with ischaemia, perforation or failed decompression → emergency laparotomy or laparoscopy:
- Reduce the stomach (decompress first with a needle if needed)
- Resect necrotic stomach → partial or subtotal gastrectomy
- Correct the cause → repair the hiatus hernia or diaphragm
- Gastropexy → anterior wall fixed to the abdominal wall, or gastrostomy tube
- Chronic volvulus → elective laparoscopic hiatus hernia repair with gastropexy
- Bezoar → surgery (gastrotomy) for large trichobezoars, Rapunzel syndrome, obstruction, perforation, failed endoscopy; check the small bowel
- Foreign body → surgery for perforation, obstruction, bleeding, failed endoscopy, sharp object not moving for 3 days, magnets with signs, ruptured drug packets or obstruction in body packers
10. Complications
- Volvulus → gastric necrosis, perforation, shock; mortality 30–50% for acute strangulated cases (historical), about 15% today
- Bezoar → gastric ulcer, bleeding, gastric outlet obstruction, perforation, small bowel obstruction, recurrence
- Foreign body:
- Oesophageal perforation → mediastinitis
- Button battery → oesophageal necrosis, tracheo-oesophageal fistula, aorto-oesophageal fistula (fatal bleeding), strictures, vocal cord palsy
- Magnets → fistula, perforation, volvulus
- Aspiration, airway obstruction
- Drug packer → fatal overdose
Show as a list
Stomach: volvulus and more
- Volvulus
- Organoaxial: 2/3
- Mesenteroaxial: 1/3
- Hiatus hernia
- Borchardt's triad
- Decompress, gastropexy
- Gastroptosis
- Thin women
- Standing barium
- Conservative
- Bezoars
- Phyto: after surgery
- Tricho: hair, Rapunzel
- Enzymes, Coca-Cola
- Endoscopy, gastrotomy
- Foreign bodies
- Children 80%
- 80-90% pass
- Button battery: emergency
- Magnets
- Sharp: urgent
- Body packers: no endoscopy


